

Lamellar Macular Hole: Symptoms, Scans and Treatment Choices
Straight lines that look slightly bent, a soft blur in the middle of a page, or letters that lose their sharp outline can all be signs of a lamellar macular hole. Some patients notice these changes in one eye, while others have no symptoms at all. Either way, a change at the very centre of the retina can raise questions about your reading and everyday vision.
This guide explains what the condition is, how it is identified, and when retinal surgery and ongoing care may form part of the plan.
Quick Overview
- A lamellar macular hole is a partial-thickness defect at the centre of the retina that does not pass through every retinal layer.
- It tends to form when traction or long-standing swelling weakens the central retinal tissue.
- Most patients are over 50, and the condition appears more often in eyes with an epiretinal membrane or previous cataract surgery.
- Management ranges from regular retinal scans to vitrectomy surgery, depending on symptoms and whether the hole changes over time.
The sections below explain each of these points in more detail.
What is a lamellar macular hole?
A lamellar macular hole is a partial-thickness break in the fovea, the small pit at the centre of the macula that gives you sharp central vision. The inner layers of the retina are affected, while the outer retinal layers beneath remain, although they can show damage. This is the main feature that separates it from full-thickness macular holes.
The macula is the part of the retina you use for reading, recognising faces and seeing fine detail. At its centre, the fovea normally has a smooth, shallow dip. In a lamellar hole, part of the inner fovea is lost, leaving a cavity with undermined edges and an irregular foveal contour on a scan.
How does a lamellar hole differ from a macular pseudohole?
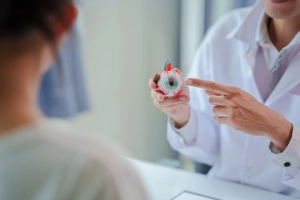 Both conditions can look like a hole during an eye examination, but only a lamellar macular hole involves true loss of retinal tissue. A macular pseudohole forms when an epiretinal membrane, a thin sheet of tissue on the retinal surface, contracts around the fovea and steepens its shape, without any tissue being lost.
Earlier research described lamellar holes as two distinct clinical entities, one driven by traction and one by slower degeneration. Current classification separates three conditions on retinal scans: the lamellar macular hole, the macular pseudohole, and epiretinal membrane foveoschisis, in which the retina splits under a contracting membrane.
The condition once called a degenerative lamellar macular hole is now simply called a lamellar macular hole. It is often accompanied by epiretinal proliferation, a thick, soft layer of material on the retinal surface that does not appear to pull on the retina the way a typical membrane does.
On a scan, pseudoholes and foveoschisis may show small cyst-like spaces in a middle retinal layer called the inner nuclear layer, while the split in a lamellar hole often lies within the outer plexiform layer. Each condition behaves differently over time, so the outlook and management also differ.
What causes a lamellar macular hole to develop?
Most lamellar holes begin with a pulling force at the fovea or with long-standing swelling in the macula. Traction from the vitreous gel or an epiretinal membrane can disrupt the supporting cells at the centre of the retina, and chronic swelling can cause the thin roof of a fluid-filled cyst to give way.
The vitreous is the clear gel that fills the eye, and it can gradually separate from the retina. If the gel keeps its attachment at the fovea as it separates, a small cyst can form in the inner retina, and its inner wall may be torn away when the gel releases.
Chronic macular swelling linked to diabetic eye disease, retinal vein occlusion or age-related macular degeneration (AMD) can also contribute. Significant short-sightedness, known as high myopia, adds traction to the macula and can play a part in the development of a lamellar hole. When no underlying cause is identified, the hole is described as idiopathic.
Most patients are over 50 at diagnosis. In population studies, lamellar holes were found more often in eyes that had previous cataract surgery, and the presence of an epiretinal membrane was also linked to them. These links point to possible risk factors rather than proven causes.
What symptoms might you notice?
Many lamellar holes cause few or no noticeable symptoms. When symptoms occur, they usually affect central vision in one eye, with mild blurring, bent straight lines, or a faint spot in the centre of what you are looking at. Visual acuity is typically only mildly reduced.
The same symptoms also occur with several other conditions of the macula, so symptoms alone cannot distinguish between them.
How is a lamellar macular hole diagnosed?
Diagnosing a lamellar macular hole relies on a retinal scan called optical coherence tomography (OCT), which uses light to produce cross-sectional images of the retinal layers. An eye examination on its own is poor at separating similar macular conditions, which is why the scan is central to the assessment.
On the scan, your ophthalmologist looks at the shape of the fovea, the edges of the defect, the thickness of tissue remaining at its base, and any membrane or epiretinal proliferation on the surface. Particular attention goes to the ellipsoid zone, a thin band in the outer retina linked to photoreceptor health and visual acuity. These findings help your ophthalmologist differentiate a lamellar hole from a pseudohole or an early full thickness hole.
Will a lamellar macular hole get worse?
 Many lamellar holes remain stable over long periods, and not everyone sees a change in vision. Others change slowly through thinning of the foveal tissue at the base, enlargement of the cavity, or disruption of the outer layers. A small number progresses to a full-thickness macular hole.
Progression cannot be predicted from a single scan, so repeat imaging over time is needed to determine whether the hole is changing.
If you notice a new central dark spot, more distortion or a drop in sight before your next scan, contact the clinic to discuss whether an earlier review is needed.
Treatment options for a lamellar macular hole
When vision is stable, and scans show no change, the hole is monitored with repeat scans.
When surgery may be discussed
Surgery may be considered when vision declines, distortion interferes with daily tasks, or scans show progressive thinning. The operation is a vitrectomy, in which the vitreous gel is removed from inside the eye. Any membrane or proliferation on the retinal surface is then carefully lifted away.
What the evidence shows
The evidence for surgery remains limited, and it remains unclear whether surgery improves vision. Where surgery is performed, operated eyes can show gradual restoration of the outer retinal layers, with healing sometimes continuing into the second year. Results vary between individuals.
Surgical risks include the chance of the membrane peel leading to a full thickness hole. Your surgeon will explain these risks alongside what a vitrectomy can and cannot achieve for your eye.
Arrange an assessment of your macula
Because a lamellar hole sits at the centre of your vision, planning care depends on an accurate picture of its structure. At Mornington Peninsula Eye Clinic, our ophthalmologists assess the structure of the fovea, provide ongoing monitoring of retinal conditions, and explain whether observation or vitrectomy suits your findings. Every recommendation follows a thorough assessment and a clear discussion of the risks involved. To arrange a consultation, please call us on (03) 9070 3580.
Frequently Asked Questions
Can a lamellar macular hole close on its own?
Spontaneous closure has been reported in some eyes, sometimes as a layer of tissue on the retinal surface extends across the defect over time. Because the natural course of lamellar holes is still poorly understood, possible closure is not a reason to skip recommended follow-up.
Does a lamellar macular hole affect both eyes?
It usually affects one eye, and a lamellar hole in both eyes is relatively uncommon. The other eye often shows changes where the vitreous gel meets the retina, most commonly an epiretinal membrane, which is a thin sheet of tissue on the retinal surface. For this reason, your ophthalmologist may check both eyes.
Is a lamellar macular hole the same as macular degeneration?
No. Age-related macular degeneration is a separate disease of the macula, while a lamellar hole is a structural defect in the inner fovea. Having one does not mean you have the other, and each is assessed and managed in its own way.
Will I need to lie face down after surgery?
Not always. Head positioning is generally linked to whether a gas bubble is placed in the eye at the end of the vitrectomy, and it is not required in every case. Your surgeon will explain the plan for your operation, including any positioning, before your operation.
Does epiretinal proliferation change how a lamellar macular hole is treated?
It can make surgery more delicate. Epiretinal proliferation is a soft, sticky tissue on the retinal surface that can be difficult to remove, and it generally needs to be lifted before the layer beneath it can be peeled. Its effect on results after surgery is still unclear.
Any surgical or invasive procedure carries risks. Before proceeding, you should seek a second opinion from an appropriately qualified health practitioner.
References
https://link.springer.com/article/10.1007/s00417-024-06419-8
https://www.nature.com/articles/s41433-022-02086-3



Leave a Reply
Want to join the discussion?Feel free to contribute!